
Office visits (99202–99215) are the highest-volume codes most practices bill, so even a small denial rate adds up fast. The good news: most E/M denials come from a short list of repeat problems, and nearly all of them can be prevented at the front desk or in the note. Here are the most common office visit denials, why they happen, and how to fix them.
1. New patient billed for an established patient
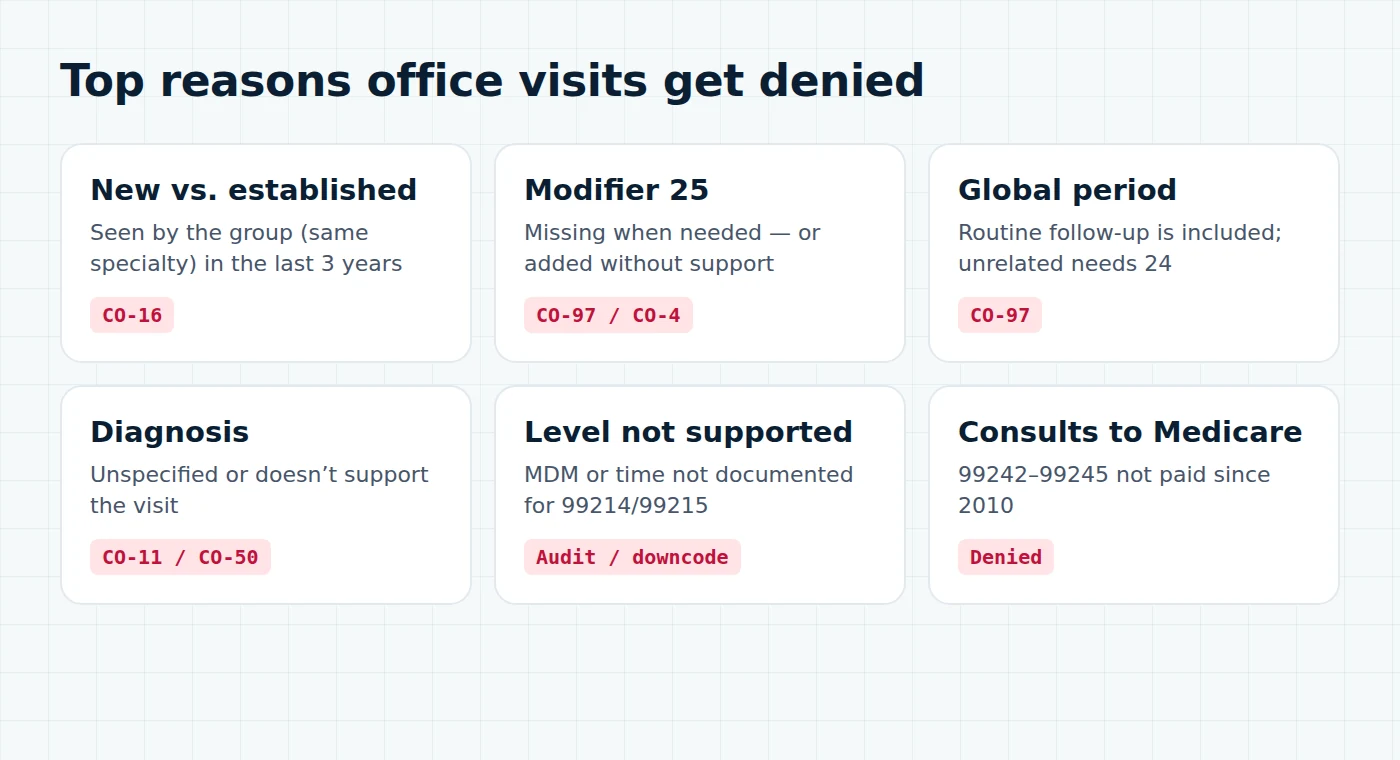
Typical denial: CO-16 or a payer-specific edit saying “new patient code not allowed.”
A patient is established if they received any professional service from the same physician or QHP, or another physician of the same specialty and subspecialty in the same group, within the past three years. That includes a visit at a different location of the same group.
Fix: check the patient’s history across the whole group before choosing 99202–99205. If they were seen within three years, rebill with 99212–99215.
2. Modifier 25 problems with same-day procedures
Typical denials: CO-97 (included in the procedure) or CO-4 (modifier issue).
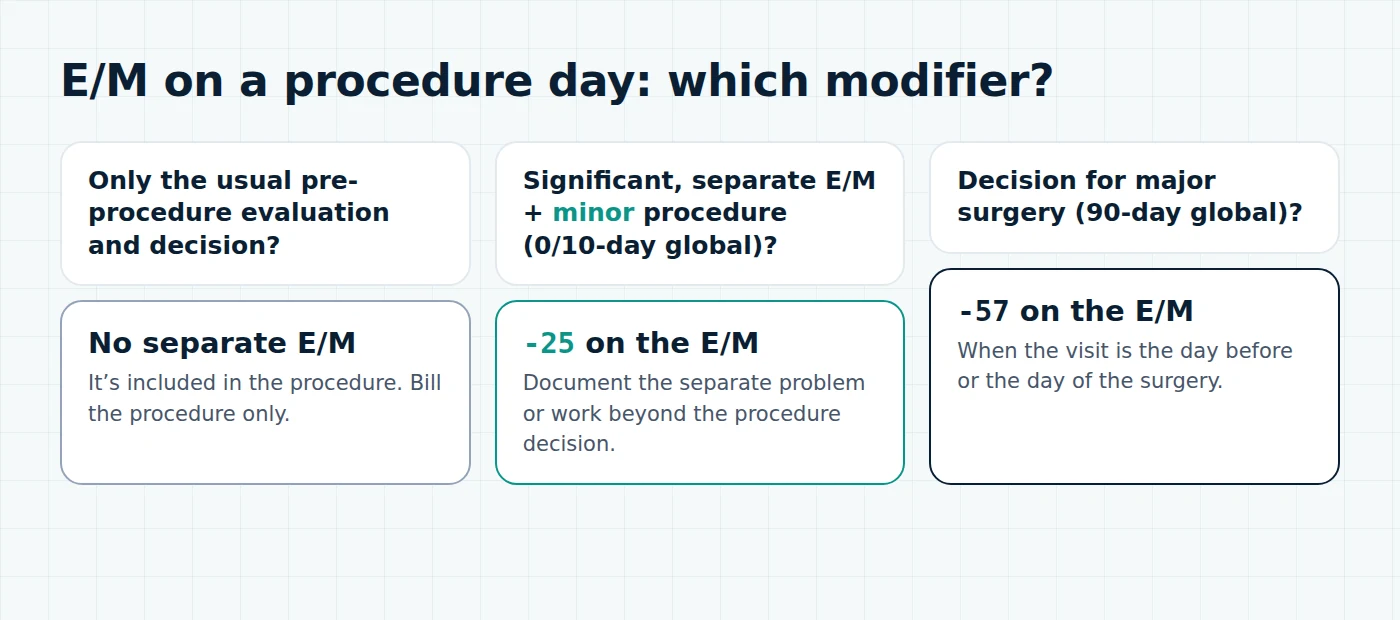
Every procedure includes a basic evaluation and the decision to do it. An E/M on the same day is only separately payable if it’s significant and separately identifiable, for example when another problem was addressed or the work clearly went beyond the pre-procedure assessment.
- Missing 25 when the E/M was truly separate leads to an automatic bundle.
- Adding 25 by default when the note doesn’t support it risks takebacks on audit.
- For a decision to perform a major surgery (90-day global) the day before or day of surgery, use 57, not 25.
3. Visit inside a global surgical period
Typical denial: CO-97.
Routine follow-up visits during a procedure’s global period (10 or 90 days) are included in the surgical payment. A visit for an unrelated problem during the postoperative period needs modifier 24, with a diagnosis that shows it’s unrelated.
Fix: flag patients in a global period at scheduling, and code the unrelated visit with 24 and the correct diagnosis.
4. Preventive and problem visit on the same day
When a patient comes in for a preventive exam and a significant problem is also addressed, both can be billed: the preventive code (for example 99395) plus a problem-oriented E/M with modifier 25, each with its own diagnoses.
- Medicare: routine physicals (99381–99397) are statutorily excluded. Medicare covers the Annual Wellness Visit (G0438 initial, G0439 subsequent) and the one-time Welcome to Medicare visit (G0402) instead. Billing 99397 to Medicare without a GY modifier and patient notice usually leads to a denial the patient may dispute.
- Only count the extra work for the problem visit. Don’t repeat the preventive history and exam elements.
5. Diagnosis doesn’t support the visit
Typical denials: CO-11 or CO-50.
Vague or incomplete diagnoses, such as unspecified codes when the note supports more detail, or symptoms coded when a definitive diagnosis exists, trigger medical necessity edits.
Fix: code to the highest specificity the documentation supports, link each diagnosis to the right line, and put the reason for the visit first. You can check specificity in our ICD-10 code search.
6. Level not supported: downcoding and audits
Payers increasingly review or automatically adjust higher-level visits (99214, 99215, 99204, 99205). The level must be supported by either MDM (two of three elements) or total time on the date of service.
- Problems listed but not addressed don’t count toward MDM.
- “Prescription drug management” needs evidence of an actual decision about the medication.
- Time-based visits need the total minutes and what the time was spent on.
See our E/M coding guidelines for 2026 for the full MDM and time rules.
7. Consultation codes billed to Medicare
Medicare hasn’t paid consultation codes (99242–99245 office, 99252–99255 inpatient) since 2010. Bill Medicare consults with the appropriate office or hospital visit codes instead. Many commercial payers still accept consult codes, so check each payer’s policy.
8. Prolonged service and add-on code errors
- Wrong prolonged code: Medicare uses G2212 (first unit at 89 minutes with 99205, 69 minutes with 99215). CPT payers use 99417 (75 and 55 minutes). Billing the wrong one is an automatic denial.
- G2211 with modifier 25: Medicare generally doesn’t pay G2211 when the visit carries modifier 25, except when the same practitioner also furnishes an annual wellness visit, vaccine administration, or Part B preventive service that day.
9. Incident-to billing errors
Billing an NPP’s visit under the physician’s NPI (“incident-to”) in the office requires, among other things, an established patient with a plan of care started by the physician, and direct supervision by a physician in the group. New patients and new problems don’t qualify. If the requirements aren’t met, bill under the NPP’s own NPI.
Office visit denial prevention checklist
- Verify eligibility and benefits before the visit, including copay and deductible.
- Check new vs. established status across the whole group (3-year rule).
- Flag patients in a global surgical period.
- Document MDM or total time clearly, and link each problem to an assessment and plan.
- Use 25, 24, 57, and G2211 only when the note supports them.
- Match prolonged codes and consult rules to the payer (Medicare vs. commercial).
- Scrub the claim before submission. Our free claim scrubber catches modifier and diagnosis pointer errors.
Seeing the same E/M denials every month? Request a free 48-hour audit and we’ll show you where the revenue is leaking.